
Europe

Marketing Communication. Capital at risk. For Professional Investors Only.
Biotechnology has spent years promising faster research and more precise treatment. In 2026, that promise began to take shape in laboratories, late-stage trials and corporate investment. AI is helping scientists develop designs they can test in the lab, while genetic information is being used to monitor cancer and develop personalised treatments.¹,²
The evidence now extends further along the development path. AI-designed proteins have bound their intended targets in laboratory tests.³ An AI-enabled drug candidate for a lung disease has entered Phase 3, and Merck and Moderna have reported positive topline Phase 3 results for a personalised cancer treatment.⁴,⁵
Companies are changing how research is organised. Anthropic has built a biology laboratory where scientists test ideas generated with Claude. Roche says it has begun building autonomous AI laboratories.⁶,⁷ AI is moving closer to the experiments that determine which ideas merit further study.⁸
These developments give the biotechnology theme a wider base. This paper updates our earlier analysis, The Platform Shift: AI, Genomics and the Patent Cliff Transforming Biotech M&A, in light of recent laboratory results, clinical developments and investment activity.
AI is beginning to move ideas from a computer into the laboratory. OpenAI introduced GPT Rosalind in April to help scientists search research, develop hypotheses and plan experiments.¹⁴ By September, the model was available globally to eligible organisations, with OpenAI working alongside Amgen, Moderna, Thermo Fisher Scientific and the Allen Institute.¹⁵,¹⁶
In August, Claude models designed proteins intended to bind to a range of targets.¹⁷ Adaptyv Bio and Twist Bioscience produced and tested the designs, confirming binders for 14 of the 15 targets that could be evaluated.¹⁸ Further studies would be needed to assess their therapeutic potential.
The next challenge is making that process routine. Reuters reported in September that Anthropic had built a biology laboratory in the San Francisco Bay Area, where scientists can test ideas generated by Claude and explore AI-directed robotic equipment under human oversight.¹⁹
Adoption is widening among established drugmakers. Novo Nordisk and Anthropic announced a collaboration in September covering medicine discovery and software development.²⁰ Roche went further and said it had begun building autonomous AI laboratories and reported that 40 percent of pipeline decisions from the fourth quarter of 2025 through the second quarter of 2026 had a tracked AI or computational contribution.²¹,²² It expects its Target Nexus tool to contribute to 80 percent of research portfolio decisions by the end of 2026.²³ These figures show how quickly AI is entering research decisions. Its effect on clinical outcomes remains to be established.
Pharmaceutical companies are also committing capital to faster research. Eli Lilly agreed to pay Insilico Medicine $115 million upfront to search for treatments across several disease areas, with the agreement potentially reaching about $2.75 billion if development and sales milestones are met.²⁴
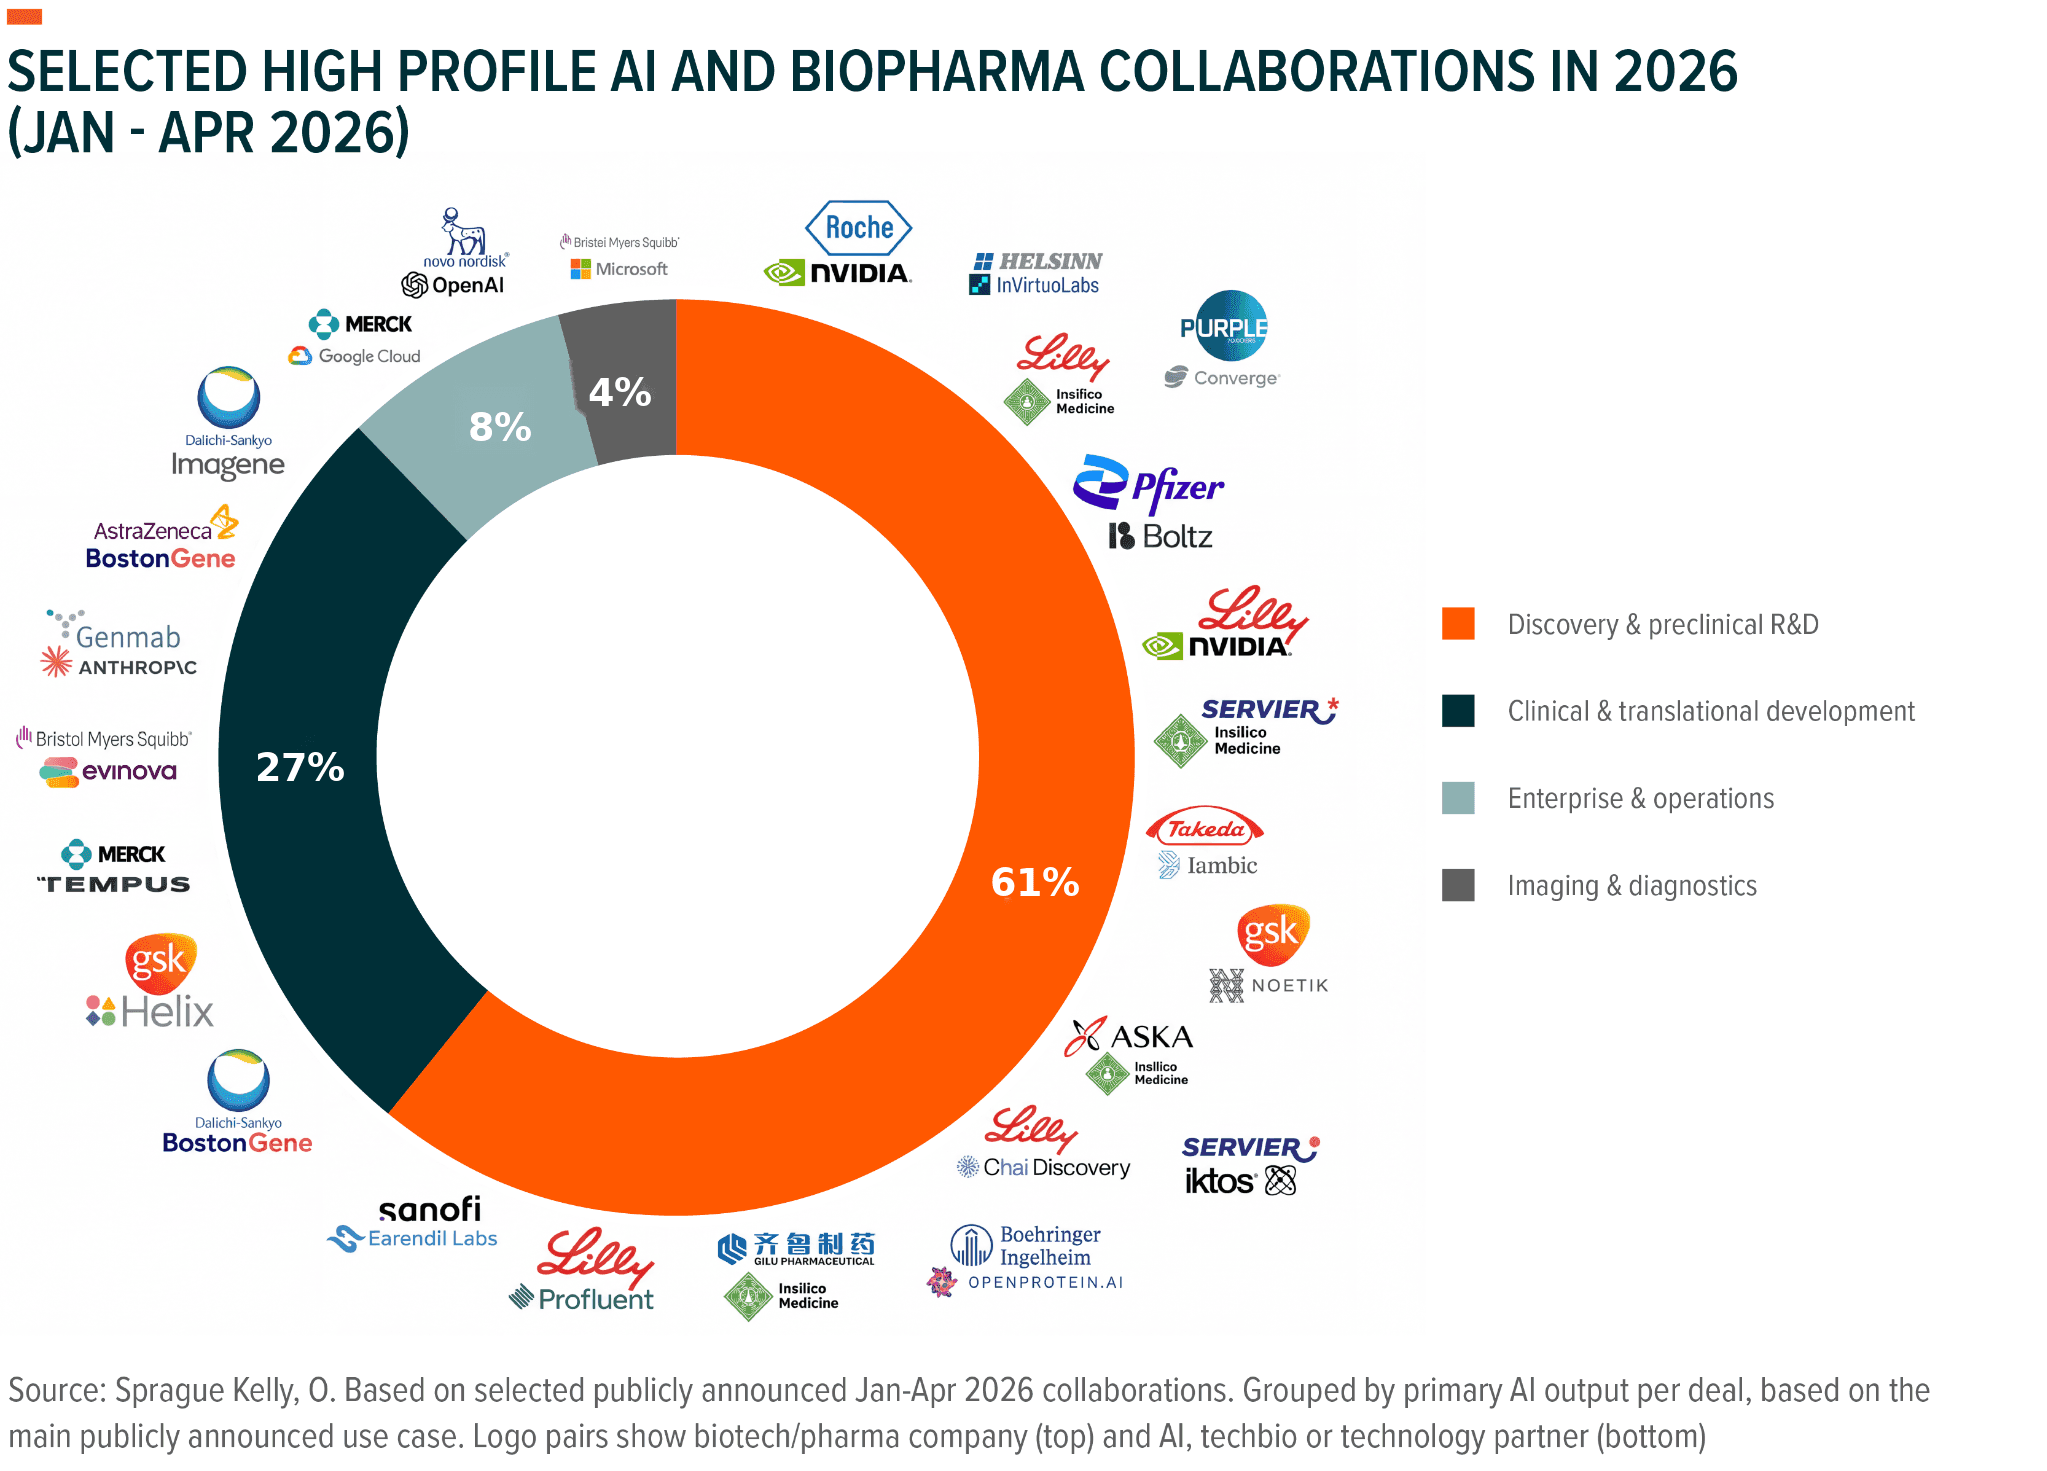
McKinsey found that selected AI-enabled programmes reached first-in-human or equivalent preclinical milestones 15 to 80 percent faster than relevant large-pharma benchmarks.²⁵ Yet most AI-native clinical assets remain in Phase 1 or Phase 2, so their effect on later clinical success is still unclear.²⁶
Insilico's lead drug, rentosertib, offers a more advanced test.²⁷ The AI-enabled candidate is being developed for idiopathic pulmonary fibrosis (IPF), a disease that scars the lungs. The first patient in its Phase 3 trial received a dose on 10 September.²⁸ In a 12-week Phase 2a study of 71 patients, the highest-dose group improved by an average of 98.4 mL on a lung-function test, compared with a 20.3 mL decline in the placebo group.²⁹ The Phase 3 trial is expected to enrol 320 patients in China and will track lung function over 52 weeks, testing whether that early signal persists in a larger and longer study.³⁰
The clearest recent genomics milestone came from Moderna and Merck. Their Phase 3 study tested intismeran, a personalised treatment designed from the genetic sequence of each patient’s tumour, in combination with Keytruda.³¹ The study involved 1,137 people whose high-risk melanoma had been removed by surgery.³² Adding intismeran to Keytruda extended the time patients remained free from recurrence or spread compared with Keytruda alone.³³ The medicine teaches the immune system what to attack, while Keytruda then helps the immune system act on that information by releasing a brake that cancer can exploit. Producing individualised medicines for hundreds of participants could indicate that personalised manufacturing can operate at meaningful clinical-trial scale.³⁴
Delivering such a treatment also requires diagnostic infrastructure. In October, Tempus expanded its collaboration with Moderna and Merck to manage the collection and transfer of tumour and blood samples. Subject to regulatory approvals, Tempus will also provide genetic sequencing to support the design and manufacture of intismeran as the companies prepare for possible commercial use.³⁵ Important evidence is still missing. The Phase 3 result is promising, but the companies have yet to publish the detailed data. Whether patients live longer remains under study, and commercial use still requires regulatory approval.
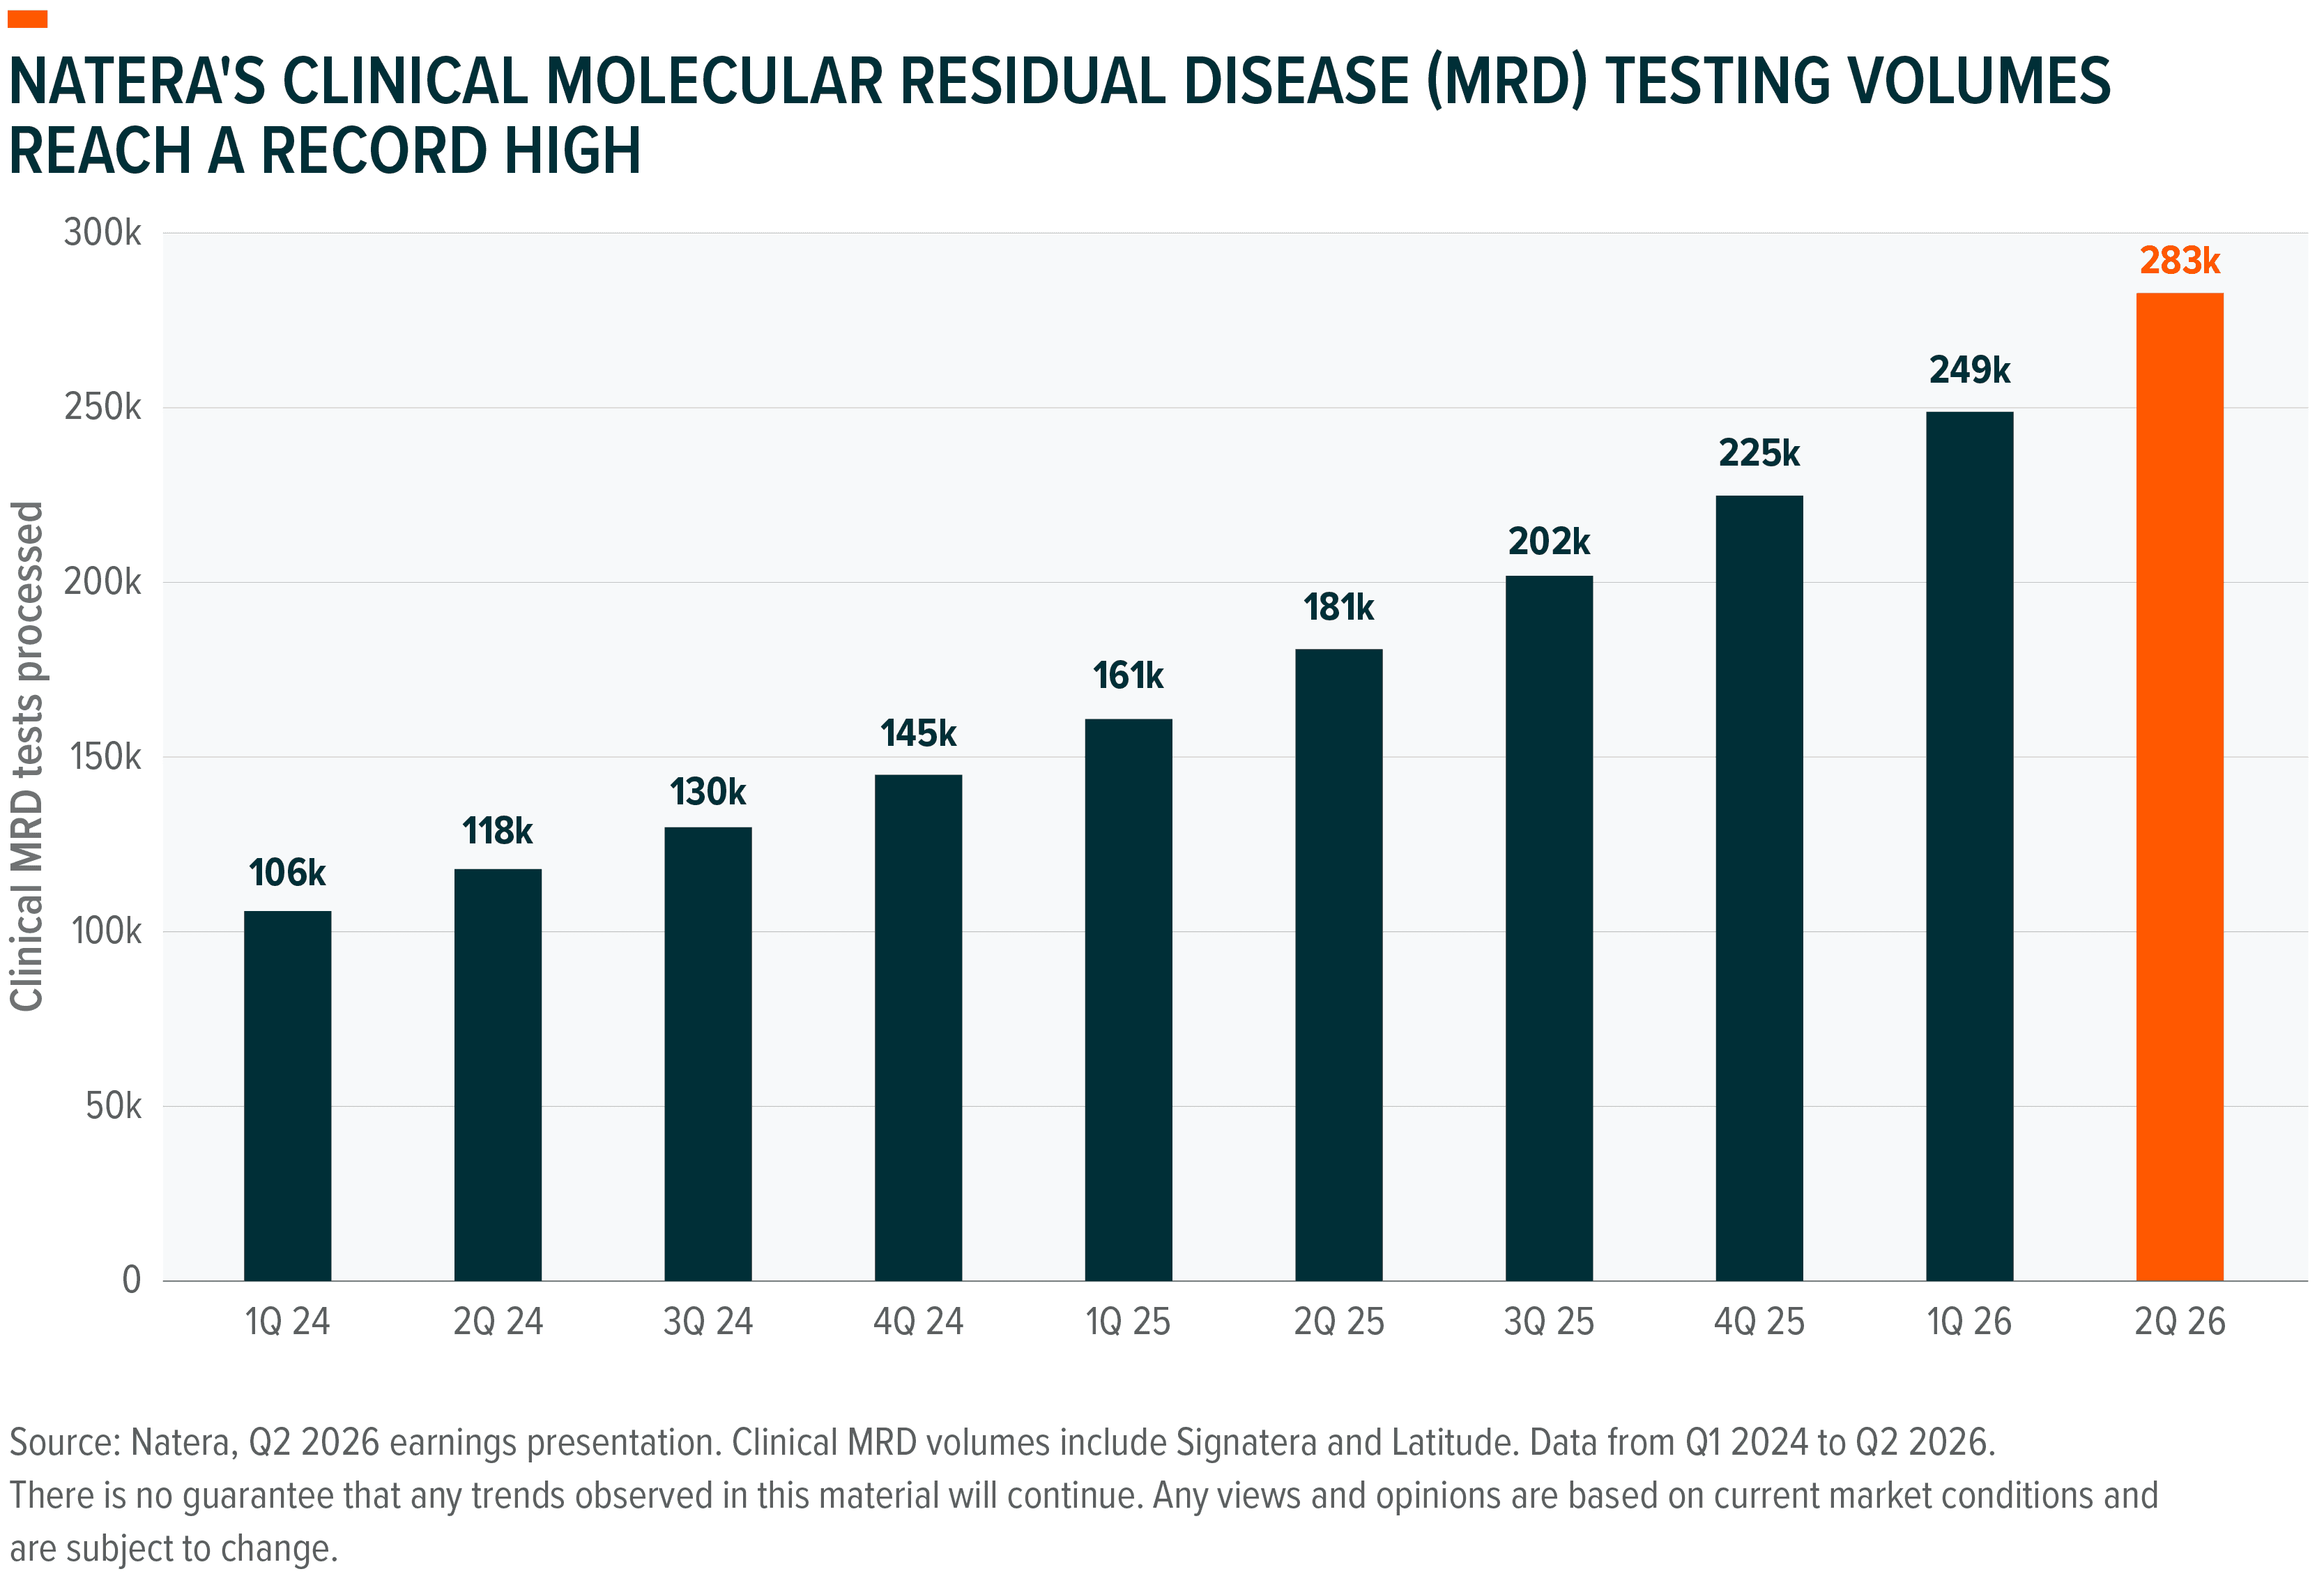
The commercial opportunity also extends to monitoring patients after treatment. Natera processed approximately 57% more oncology tests in the second quarter of 2026 than a year earlier.³⁶ These blood tests detect fragments of tumour DNA that may remain after surgery or treatment, potentially warning doctors earlier that cancer is returning.³⁷ Total revenue rose 37.7 percent to $752.8 million, and the company raised the midpoint of its annual revenue guidance by $100 million.³⁸
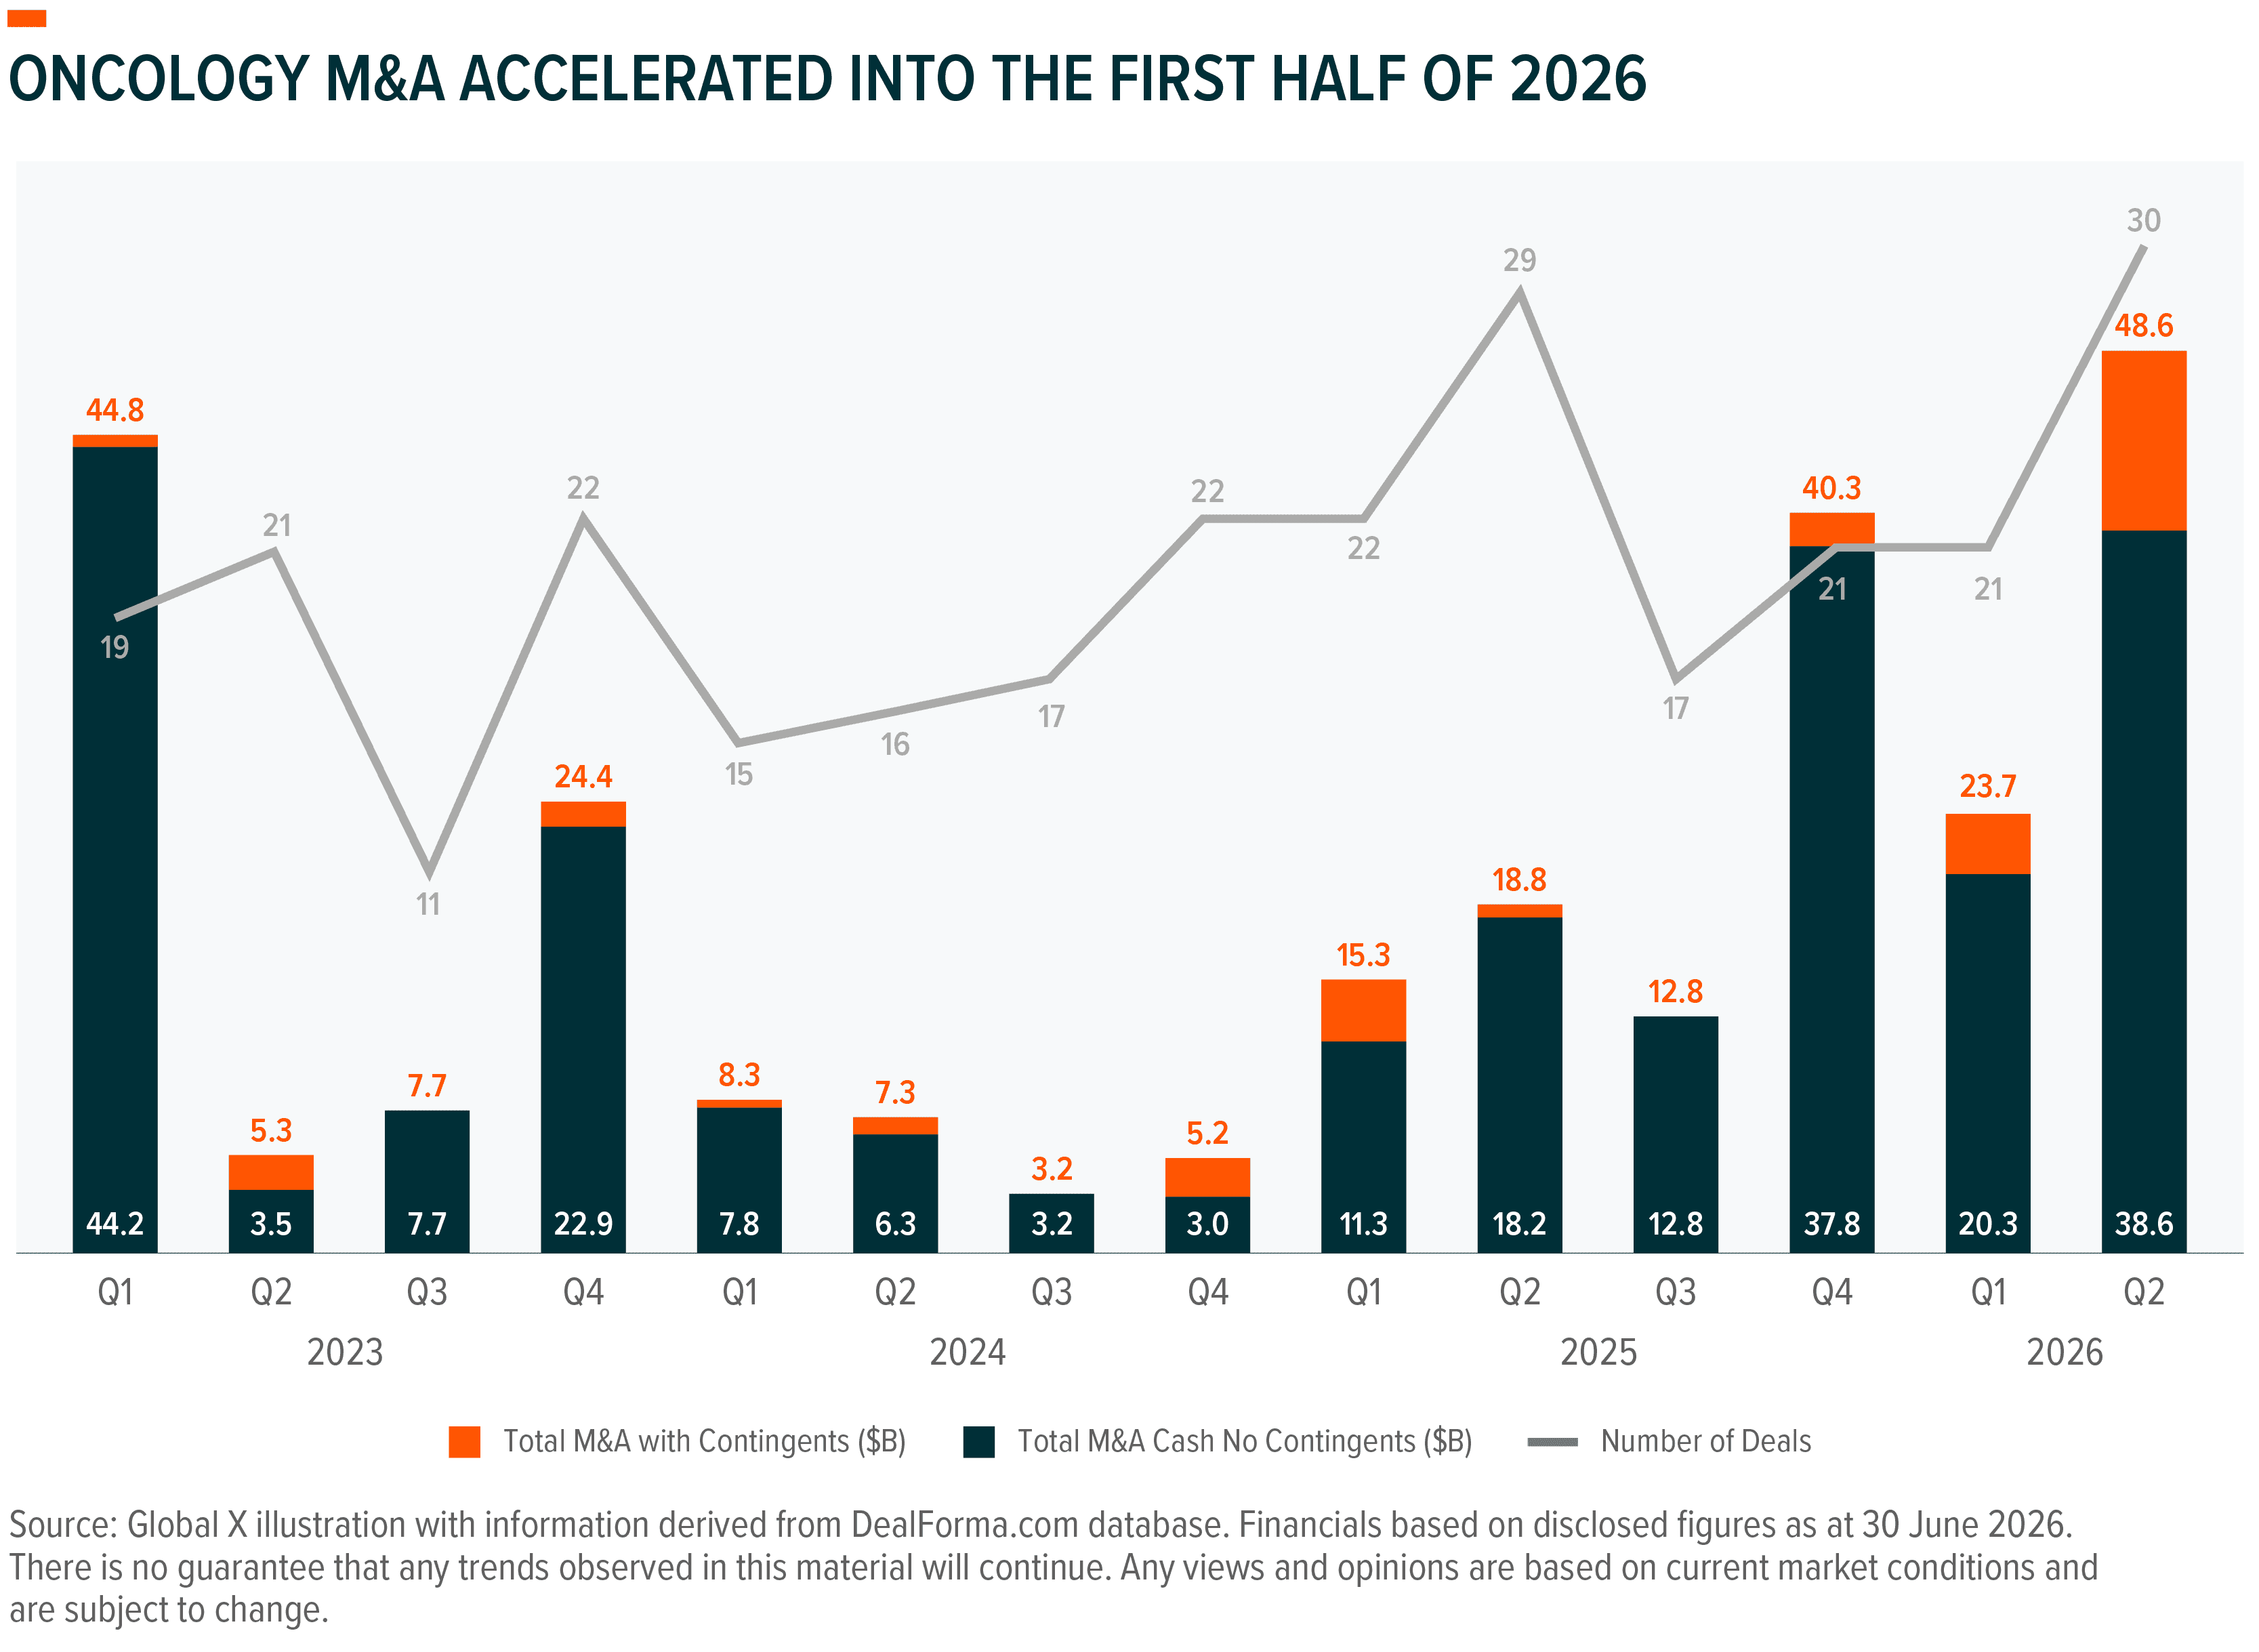
The business pressure behind biotechnology deals remains straightforward. When a successful medicine loses patent protection, lower-priced competitors can enter and sales can fall quickly. Several major products face this point by 2030.³⁹ Internal research rarely produces enough replacements on the required timetable, so large drug companies continue to buy or license medicines developed elsewhere.⁴⁰ Smaller biotechnology companies still face costly financing, making a well-capitalised buyer especially important.⁴¹
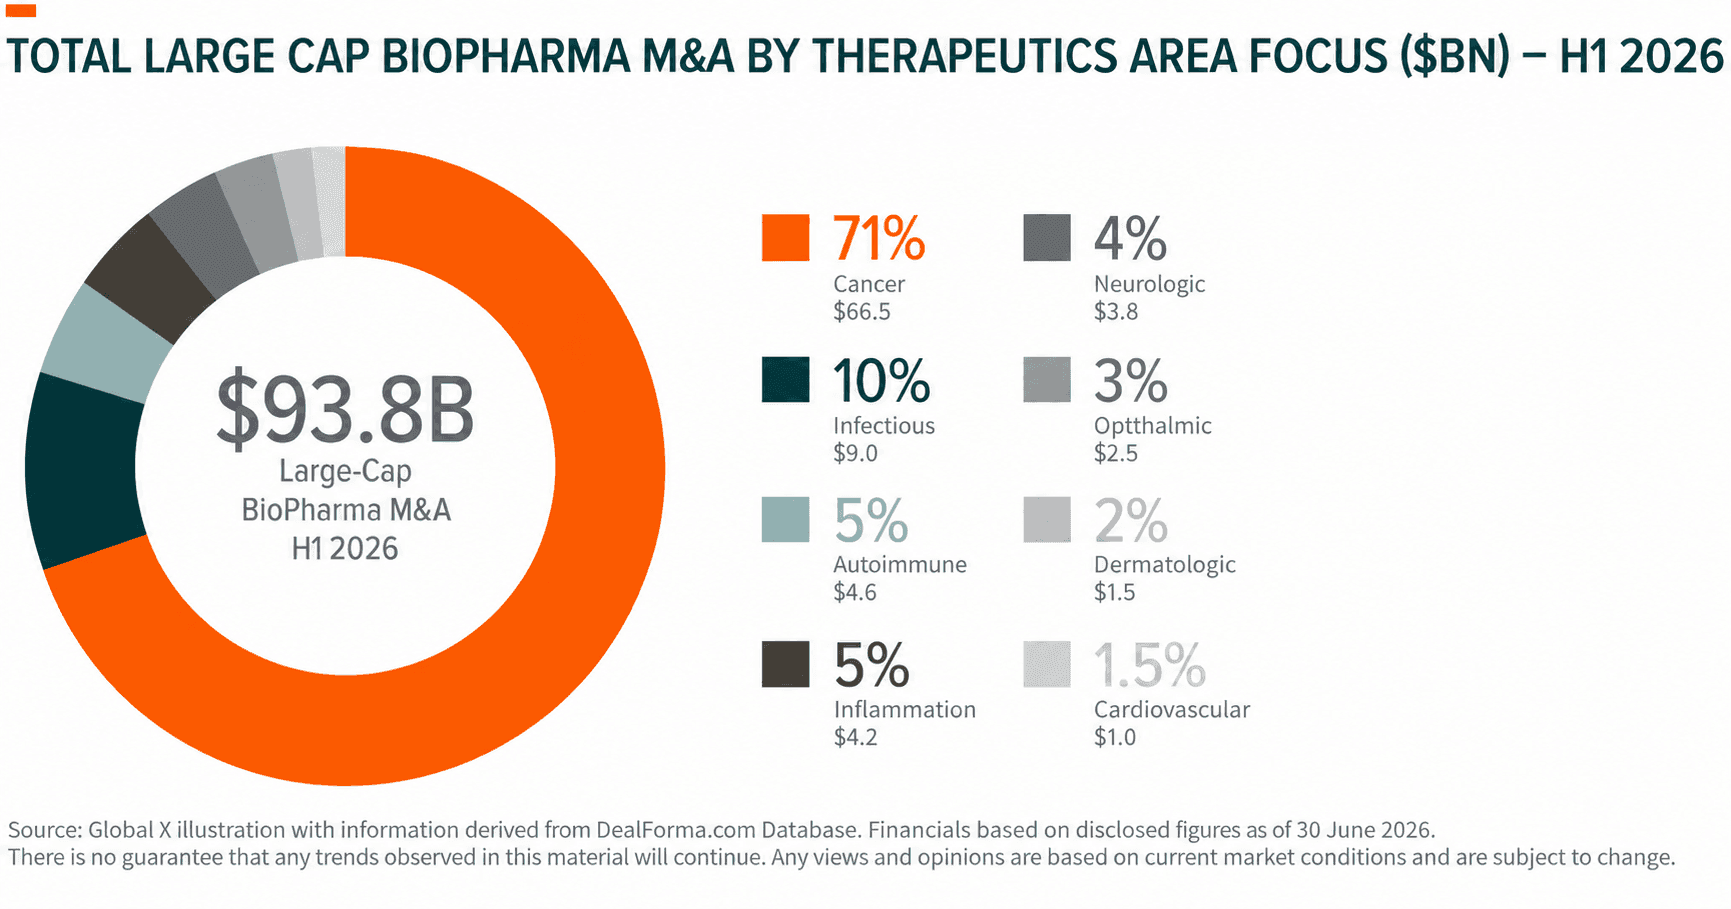
Oncology attracted a particularly large share of this capital. Cancer-focused transactions represented $66.5 billion, or 71%, of the $93.8 billion in disclosed large-cap biopharma M&A during the first half of 2026.⁴²
BioWorld recorded an overall $186.69 billion of biopharma deal value in the first seven months of 2026, 13% more than a year earlier, while completed transactions fell to 674 from 718.⁴³ Buyers appear willing to spend on fewer programmes with clearer evidence or a strong fit with existing expertise.
Laboratory results, clinical trials and new deals give investors more evidence with which to assess biotechnology’s progress. The next clinical results will show which approaches benefit patients. Their commercial value will also depend on regulatory approval and the ability to manufacture and deliver treatments at a viable cost.
This document is not intended to be, or does not constitute, investment research as defined by the Financial Conduct Authority.